What is the best treatment for Evans Syndrome - Health Benefits
Evans syndrome is a rare and chronic autoimmune disorder in which the immune system mistakenly attacks and destroys the body’s own healthy blood cells. The condition is defined by the simultaneous or sequential development of at least two immune-mediated blood conditions: autoimmune hemolytic anemia (the destruction of red blood cells) and immune thrombocytopenia (the destruction
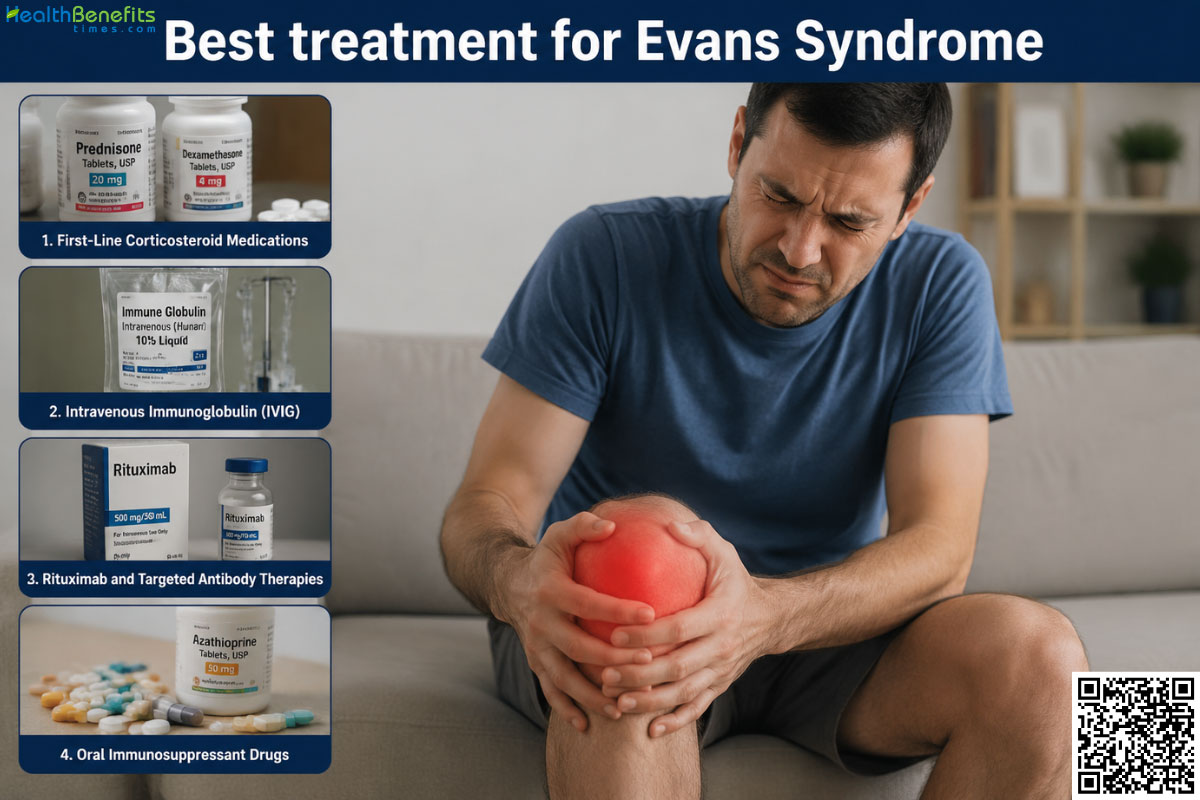
Evans syndrome is a rare and chronic autoimmune disorder in which the immune system mistakenly attacks and destroys the body’s own healthy blood cells. The condition is defined by the simultaneous or sequential development of at least two immune-mediated blood conditions: autoimmune hemolytic anemia (the destruction of red blood cells) and immune thrombocytopenia (the destruction of platelets) (Audia et al. , 2020)1. In some cases, the condition also targets white blood cells, leading to autoimmune neutropenia (Fattizzo et al. , 2021)2. Consequently, patients frequently experience severe fatigue, paleness, unexplained bruising, and an increased risk of bleeding. While the exact cause remains largely unknown, the syndrome can occur idiopathically or secondary to other systemic autoimmune diseases, primary immunodeficiencies, or lymphoproliferative disorders (Jaime-Pérez et al. , 2018)3. Because of its complex and relapsing nature, Evans syndrome requires careful, individualized medical management, most commonly beginning with corticosteroids to suppress the overactive immune response (Fattizzo et al. , 2024)4. Causes of Evans SyndromeEvans syndrome occurs when the immune system produces antibodies that mistakenly attack and destroy the body’s own healthy blood cells. Medical professionals classify the causes of this immune system malfunction into two main categories: primary and secondary. Primary (or idiopathic) Evans syndrome means that the condition develops independently without any identifiable underlying cause. In contrast, secondary Evans syndrome is triggered by another existing medical condition, genetic defect, or external infection. The known underlying causes and triggers of secondary Evans syndrome include:Systemic Autoimmune Diseases: Existing autoimmune conditions, where the body’s immune system attacks healthy tissues, can trigger the syndrome. Systemic lupus erythematosus (SLE) is the most frequently associated autoimmune disease, though it can also occur alongside rheumatoid arthritis and autoimmune hepatitis (Jaime-Pérez et al. , 2018)3. Primary Immunodeficiencies: These are inherited immune system disorders that prevent the body from fighting off threats properly. Conditions such as autoimmune lymphoproliferative syndrome (ALPS) and common variable immunodeficiency (CVID) are common underlying causes of the syndrome, particularly in young children (Shaikh, n. d. )5. Specific Genetic Mutations:Inherited errors in specific genes that regulate immune responses can lead to the syndrome. Deficiencies in vital immune-regulating proteins, such as CTLA-4, LRBA, and TPP2, disrupt normal immune balance and cause severe immune dysregulation (Jaime-Pérez et al. , 2018)3. Blood and Lymph Node Cancers: Malignancies that affect the white blood cells and the lymphatic system are established causes of the syndrome, primarily in older adults. These cancers include chronic lymphocytic leukemia (CLL) and non-Hodgkin lymphoma (Carli et al. , 2016)6. Viral and Bacterial Infections: Certain infections can confuse the immune system and prompt it to attack healthy blood cells. Infectious triggers shown to cause the syndrome or provoke relapses include the Epstein-Barr virus (EBV), cytomegalovirus (CMV), hepatitis B and C, the human immunodeficiency virus (HIV), parvovirus B19, and the SARS-CoV-2 virus responsible for COVID-19 (Audia et al. , 2020)1; (Fattizzo, n. d. )7. Symptoms of Evans SyndromeThe clinical presentation of Evans syndrome varies depending on which specific blood cells the immune system attacks and the severity of the cell destruction. Individuals typically experience a combination of symptoms related to the depletion of red blood cells, platelets, and, occasionally, white blood cells. Symptoms of Autoimmune Hemolytic Anemia (Low Red Blood Cells): When the immune system destroys red blood cells faster than the bone marrow can replace them, the body’s tissues receive insufficient oxygen. This manifests as profound fatigue, general weakness, pallor (abnormal paleness of the skin), and shortness of breath during routine physical exertion. The rapid breakdown of red blood cells also releases excess bilirubin into the bloodstream, frequently causing jaundice (a yellowish discoloration of the skin and the whites of the eyes) and abnormally dark urine (Audia et al. , 2020)1. Symptoms of Immune Thrombocytopenia (Low Platelets): Platelets are specialized cell fragments essential for normal blood clotting. Their destruction leads to frequent and unexplained bleeding complications. Affected individuals often develop petechiae (tiny, non-raised red or purple dots on the skin caused by broken capillaries) and purpura (larger purple patches or severe bruising that appears without injury). Other common symptoms include frequent nosebleeds, bleeding gums, and unusually heavy menstrual periods (Jaime-Pérez et al. , 2018)3. Symptoms of Autoimmune Neutropenia (Low White Blood Cells): In roughly 15% of cases, Evans syndrome also targets neutrophils, a critical type of white blood cell responsible for fighting off bacterial and fungal infections. Patients with this depletion exhibit a severely compromised immune response, leading to a high susceptibility to frequent, recurrent infections that are often accompanied by persistent or unexplained fevers (Shaikh, n. d. )5. Systemic and Organ-Related Symptoms: The excessive destruction and filtration of abnormal blood cells force the body’s organs to work much harder than usual. This overexertion frequently leads to hepatosplenomegaly (the physical enlargement of the liver and spleen), which can cause discomfort or a persistent feeling of fullness in the upper abdomen. Patients may also develop swollen lymph nodes during active disease flares (Hussain et al. , 2019) {% https://pmc. ncbi. nlm. nih. gov/articles/PMC6497206/1. First-Line Corticosteroid MedicationsHow it may helpCorticosteroids are the established primary treatment for Evans syndrome. By directly suppressing the immune system, they reduce the destruction of red blood cells and platelets caused by abnormal autoantibodies5. This action helps restore normal blood counts, reverses severe anemia, and prevents potentially life-threatening bleeding episodes8. What research saysClinical evidence confirms that the majority of patients respond well to initial corticosteroid therapy, experiencing rapid stabilization5. However, research indicates that long-term remission is uncommon, and more than half of patients eventually relapse5. Steroids remain crucial for early intervention, though secondary immunosuppressive medications are frequently needed later3. How to use it safelyYou must take corticosteroids exactly as prescribed by your healthcare provider. The medication is typically given at a high starting dose and slowly tapered off over weeks or months5. Never stop taking this medication abruptly, as sudden withdrawal can cause dangerous complications and trigger a disease relapse. Potential precautions or side effectsProlonged corticosteroid therapy increases your susceptibility to severe infections, elevated blood sugar, weight gain, and osteoporosis3. Regular medical monitoring is essential to manage these serious adverse effects safely. 2. Intravenous Immunoglobulin (IVIG)How it may helpIntravenous Immunoglobulin (IVIG) provides rapid stabilization during severe episodes of Evans syndrome. It works by blocking the immune system’s receptors, preventing immune cells from destroying red blood cells and platelets (Giannotta, n. d. )9. This quickly increases blood cell counts, controlling life-threatening bleeding and massive hemolysis (Jaime-Pérez et al. , 2018)3. What research saysResearch indicates IVIG is a critical first-line therapy, especially when patients experience severe bleeding (Shaikh, n. d. )5. While it successfully induces rapid responses in most patients, clinical studies conclude these benefits are temporary, requiring secondary long-term immunosuppressive therapies to maintain remission and prevent relapses (Giannotta, n. d. )9. How to use it safelyYou must receive IVIG infusions strictly in a monitored medical setting. To prevent adverse reactions, your healthcare provider will administer the dose slowly and may provide premedications like antihistamines (Arumugham, n. d. )10. Stay well-hydrated before the infusion to reduce the risk of kidney strain (Arumugham, n. d. )10. Potential precautions or side effectsCommon side effects include headaches, fever, and nausea (Arumugham, n. d. )10. Seek emergency care for rare complications like severe allergic reactions, blood clots, or kidney failure (Arumugham, n. d. )10. 3. Rituximab and Targeted Antibody TherapiesHow it may helpRituximab is a targeted monoclonal antibody that identifies and destroys specific immune cells, called B-cells, which are responsible for producing harmful autoantibodies3. By reducing the number of these abnormal cells, rituximab stops the immune system from attacking red blood cells and platelets, allowing blood counts to recover11. What research saysResearch establishes rituximab as a highly effective second-line therapy for patients who do not respond to or relapse after initial corticosteroid treatment3. Clinical studies show it achieves a successful response in most patients, providing long-term remission, though some may require repeated courses if symptoms return3. How to use it safelyYou must receive rituximab through an intravenous infusion in a closely monitored clinical setting. To prevent severe allergic reactions, your healthcare provider will give you premedications, such as antihistamines and fever reducers, before each session12. Attend all scheduled blood tests to monitor your recovery. Potential precautions or side effectsCommon side effects include fever, rash, and nausea during infusion3. Because the medication depletes your immune cells, you face a significantly increased risk of severe infections for several months11. 4. Oral Immunosuppressant DrugsHow it may helpOral immunosuppressants, such as mycophenolate mofetil or cyclosporine, work by broadly dampening an overactive immune system5. By suppressing the production and activity of specific immune cells, these daily medications prevent the continuous destruction of red blood cells and platelets, steadily stabilizing blood counts over time3. What research saysClinical research identifies oral immunosuppressants as a vital second-line or steroid-sparing therapy for patients who repeatedly relapse or cannot tolerate long-term corticosteroids3. Studies conclude that while they do not cure the disease, these medications successfully maintain long-term remission and significantly reduce the need for continuous interventions13. How to use it safelyYou must take these medications consistently at the exact prescribed dose, as missing doses can trigger sudden relapses. Because these drugs suppress your immune system, you should avoid sick individuals and attend all scheduled laboratory tests to monitor your organ function and blood counts5. Potential precautions or side effectsThese drugs significantly increase your risk of severe infections, liver toxicity, and gastrointestinal distress3. Long-term use may also elevate the risk of developing certain secondary cancers5. 5. Medications to Stimulate Platelet Production (TPO-RAs)How it may helpThrombopoietin receptor agonists (TPO-RAs), such as eltrombopag and romiplostim, directly stimulate the bone marrow to increase the production of platelets3. By boosting platelet generation, these medications compensate for the rapid destruction of blood cells caused by Evans syndrome, successfully stabilizing platelet counts and preventing severe bleeding. What research saysClinical studies establish TPO-RAs as a highly effective second-line therapy for the thrombocytopenia component of Evans syndrome in patients who relapse or fail initial corticosteroid treatments14. Multicenter research demonstrates strong response rates for restoring platelets, though these drugs do not improve the autoimmune hemolytic anemia component14. How to use it safelyTake oral TPO-RAs exactly as prescribed or attend all scheduled weekly clinic visits for subcutaneous injections. You must undergo frequent blood testing during treatment so your healthcare provider can carefully monitor your platelet counts and adjust your dosage, preventing your levels from rising dangerously high14. Potential precautions or side effectsThese medications significantly increase your risk of dangerous venous and arterial blood clots15. Additional side effects include headaches, muscle pain, joint pain, and potential liver toxicity3. 6. Targeted Sirolimus TherapyHow it may helpSirolimus is a targeted immunosuppressant that works by inhibiting the mTOR pathway, calming an overactive immune system. It directly reduces the excessive activity of lymphocytes, preventing the production of harmful autoantibodies that destroy red blood cells and platelets16. This effectively stabilizes blood counts and shrinks an enlarged spleen. What research saysClinical trials establish sirolimus as a highly effective, steroid-sparing therapy for patients with relapsed or refractory Evans syndrome16. Multicenter research demonstrates that monotherapy successfully induces durable, long-term remission in most patients who fail standard treatments, proving especially beneficial for those with underlying autoimmune lymphoproliferative disorders17. How to use it safelyYou must take this daily oral medication exactly as prescribed. Attend all scheduled laboratory appointments to monitor the drug concentration in your blood. Your healthcare provider will use these routine tests to precisely adjust your dosage and maintain a safe therapeutic range18. Potential precautions or side effectsCommon side effects include mouth sores, mild hypertension, and altered liver enzymes. Because the medication reduces immune function, it increases your susceptibility to infections19. 7. Surgical Removal of the Spleen (Splenectomy)How it may helpSurgical removal of the spleen directly eliminates the primary organ responsible for trapping and destroying blood cells3. By removing this major site of cellular destruction, the procedure stops the rapid loss of red blood cells and platelets, effectively raising blood counts and resolving severe bleeding complications. What research saysClinical studies indicate that while splenectomy was traditionally a standard second-line option, its use has significantly declined due to the availability of newer targeted medications13. Research shows that while it induces temporary remission in many patients, long-term success is unpredictable, and most individuals eventually experience a relapse5. How to use it safelyBecause the spleen filters bacteria, you must receive specific vaccines against pneumonia, meningitis, and influenza weeks before the surgery20. Post-surgery, you must seek emergency medical attention for any fever, as minor illnesses can quickly escalate into fatal complications. Potential precautions or side effectsThe most severe lifelong complication is an overwhelming, life-threatening bacterial infection5. Removing the spleen also significantly increases your risk of developing dangerous internal blood clots13. 8. Hematopoietic Stem Cell TransplantationHow it may helpHematopoietic stem cell transplantation completely replaces a defective immune system with healthy stem cells. By eliminating the source of abnormal lymphocytes and generating a new, healthy immune response, this procedure can permanently stop the continuous destruction of blood cells, offering a potential cure3. What research saysResearch identifies this procedure as a rare, last-resort therapy for patients who fail all standard medical interventions5. Although it remains the only potentially curative option for refractory Evans syndrome, experts strictly reserve it for extreme cases due to high toxicity and treatment-related mortality3. How to use it safelyYou must undergo this rigorous procedure exclusively within a specialized transplant center. Before receiving new stem cells, you will require intensive chemotherapy to eliminate your existing bone marrow. Afterward, you must remain in strict medical isolation to prevent life-threatening infections while your new immune system develops. Potential precautions or side effectsThis procedure carries extreme risks. You face a high susceptibility to fatal systemic infections, severe organ toxicity, and potentially lethal graft-versus-host disease when receiving donor stem cells21. 9. Emergency Blood and Platelet TransfusionsHow it may helpEmergency transfusions deliver an immediate supply of healthy red blood cells or platelets during life-threatening crises. While not a cure, this rapid replacement prevents fatal cardiovascular collapse from severe anemia and stops catastrophic bleeding, keeping the patient stable until primary immunosuppressive medications begin working3. What research saysClinical guidelines classify transfusions as a temporary, supportive intervention strictly reserved for severe, symptomatic cases5. Research confirms that transfused cells are rapidly destroyed by the same circulating autoantibodies causing the disease, meaning survival of these donor cells is extremely short-lived and provides only transient stabilization3. How to use it safelyYou must receive transfusions strictly in a hospital under continuous medical supervision. Because your autoantibodies complicate blood typing, specialized laboratory cross-matching is required to find the safest compatible donor blood5. Report any chills, fever, or shortness of breath immediately during the procedure. Potential precautions or side effectsTransfusions risk severe allergic reactions, fluid overload, and the development of new antibodies against donor blood, which severely complicates your future treatment and cross-matching options5. Foods to Avoid When You suffer from Evans SyndromeEvans syndrome is a rare autoimmune disorder where the body mistakenly destroys its own red blood cells and platelets22. Dietary management of this condition primarily focuses on reducing the adverse side effects of standard clinical therapies. The standard treatments for Evans syndrome include corticosteroids, such as prednisone, and various immunosuppressive drugs23. Extended use of these medications frequently causes metabolic complications, including fluid retention, elevated blood sugar, and unwanted weight gain24. Furthermore, because immunosuppressive therapies significantly weaken the immune system, patients face a heightened risk of acquiring severe, opportunistic foodborne infections25. Consequently, clinical guidelines emphasize avoiding foods that interact with drug metabolism or carry high amounts of bacteria. When managing your condition, you should strictly avoid high-risk foods to protect your immune system and prevent treatment-related complications. 1. Raw or Undercooked Meat and SeafoodImmunosuppressive therapies lower your body’s natural defenses. You must avoid raw or undercooked animal products, as they frequently harbor dangerous bacteria that cause severe foodborne illness25. 2. Unpasteurized Dairy ProductsUnpasteurized milk and soft cheeses often contain Listeria, a dangerous bacterium. Consuming these products poses an extreme infection risk when your immune system is compromised by medical therapy25. 3. Grapefruit and Grapefruit JuiceGrapefruit interferes with the liver enzymes responsible for breaking down drugs. This dangerously increases the absorption and toxicity of certain immunosuppressant medications used in your treatment26. 4. High-Sodium Processed FoodsBecause prolonged corticosteroid use commonly triggers fluid retention and elevated blood pressure, you should strictly avoid heavily salted foods like canned soups, deli meats, and processed snacks24. 5. High-Sugar Foods and BeveragesCorticosteroid medications routinely cause elevated blood sugar and promote excessive weight gain. You should avoid refined sugars and sugary drinks to maintain healthy energy levels during your treatment24. When to See a Doctor When You Suffer From Evans SyndromeEvans syndrome is a rare, chronic autoimmune disorder characterized by the body’s destruction of its own red blood cells, platelets, and occasionally white blood cells. Because the condition involves unpredictable periods of remission and sudden, severe exacerbations, close medical monitoring is essential to prevent life-threatening complications27. Sudden drops in blood cell counts can trigger massive red blood cell destruction or catastrophic internal hemorrhage, both of which are leading causes of mortality requiring immediate clinical intervention3. Furthermore, the immunosuppressive therapies used to manage the disorder, alongside potential immune neutropenia, significantly heighten the risk of severe, rapid-onset infections28. While routine follow-ups are a standard part of care, certain acute clinical manifestations demand emergency evaluation. You should seek prompt medical attention if you experience sudden, unexplained, or severe symptoms that indicate a critical drop in your blood cell levels. 1. Uncontrollable or Spontaneous BleedingSeek immediate care for continuous nosebleeds, bleeding gums, blood in your urine or stool, or heavy menstrual bleeding. These indicate severe platelet destruction and carry a high hemorrhage risk29. 2. Sudden or Severe Shortness of BreathDifficulty breathing, especially while resting, can signal a dangerous drop in oxygen-carrying red blood cells or cardiovascular complications triggered by severe anemia. You require urgent clinical evaluation29. 3. Chest Pain or Rapid HeartbeatSevere anemia forces your heart to work harder to deliver oxygen. Chest discomfort or a racing pulse may indicate acute cardiac strain or inadequate blood flow28. 4. High Fever or Signs of InfectionBecause Evans syndrome and its treatments can drastically lower your protective white blood cells, a sudden fever or chills indicates an opportunistic infection requiring immediate medical treatment27. 5. Rapid Development of Bruises or PetechiaeIf you notice widespread, unexplained bruising or tiny, flat red spots on your skin, your platelet count may have dropped to dangerously low levels, increasing internal bleeding risks3. 6. Sudden Jaundice or Dark UrineThe sudden yellowing of your skin or eyes, coupled with dark urine, indicates an acute, massive destruction of red blood cells that necessitates emergency hospital intervention27. Commentscomments